

Overview
Bacterial vaginosis (BV) is the most common cause of unusual vaginal discharge in women of reproductive age. It happens when the normal balance of bacteria in the vagina is disturbed, with fewer protective lactobacilli and an overgrowth of other bacteria.
BV typically causes a thin, grey or white discharge with a strong fishy smell, especially after sex. About half of women with BV have no symptoms. It is not a sexually transmitted infection, though it is more common in sexually active women and can be linked to new or multiple partners. BV is easily treated with antibiotics, but it often comes back. Untreated BV can increase the risk of sexually transmitted infections and problems in pregnancy.
Many women feel embarrassed by the smell, but BV is very common and nothing to be ashamed of. It is easy to test for, and a sexual health clinic, GP or pharmacist can advise on treatment.
When to get urgent help
Seek prompt care for discharge with pelvic pain, fever, bleeding between periods or after sex, or if you are pregnant and have symptoms.
Causes and risk factors
- Loss of lactobacilli and overgrowth of bacteria such as Gardnerella vaginalis, Prevotella, Atopobium and Mobiluncus
- Risk factors:
- New or multiple sexual partners
- Vaginal douching and washing with perfumed products
- Smoking
- Intrauterine device (coil)
- Having a female partner with BV
- Not using condoms
- BV is not caused by poor hygiene
How it develops (pathophysiology)
Normal vaginal environment
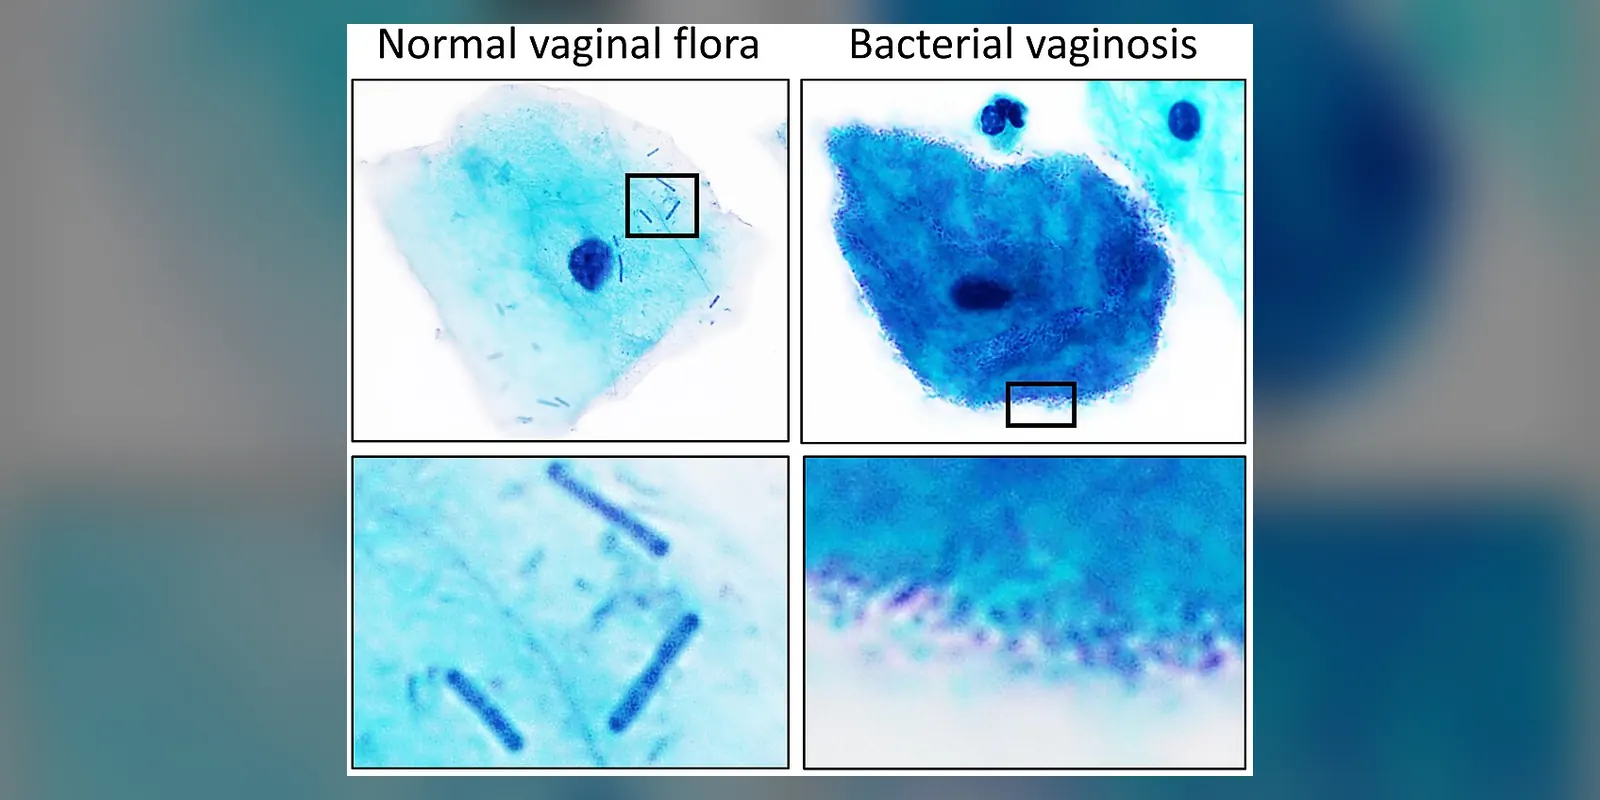
The healthy vagina is dominated by lactobacilli, bacteria that produce lactic acid, keeping the pH acidic (below 4.5). Lactobacilli also produce hydrogen peroxide and bacteriocins, which inhibit other bacteria. This acidic, lactobacillus-rich environment protects against infections.
What goes wrong
- Disruption: factors such as douching, semen (which is alkaline), new partners or hormonal changes reduce lactobacilli.
- Rising pH: with less lactic acid, the vaginal pH rises above 4.5.
- Overgrowth: anaerobic bacteria multiply up to 1,000-fold. Gardnerella vaginalis forms a biofilm, a sticky layer that attaches to vaginal cells and protects other bacteria.
- Amine production: anaerobic bacteria produce amines (such as trimethylamine), which cause the fishy smell, especially when exposed to alkaline semen.
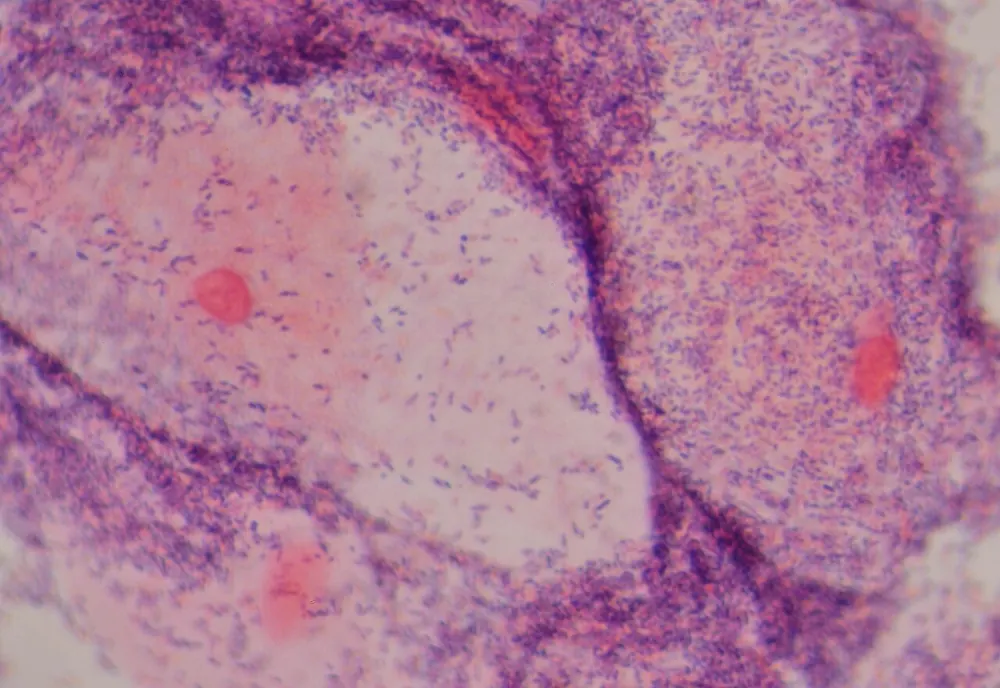
- Clue cells: vaginal cells coated with bacteria (clue cells) are shed into the discharge.
- Reduced defences: BV is associated with reduced protective factors and changes in the immune environment, increasing susceptibility to sexually transmitted infections, including HIV.
Unlike many infections, BV causes little inflammation, which is why itching and soreness are not typical.
Why the symptoms happen
- Thin, grey or white discharge results from bacterial overgrowth and shed cells.
- Fishy smell comes from amines.
- Smell worse after sex or during periods occurs because semen and blood raise pH, releasing more amines.
- Itching and irritation are uncommon and suggest another cause, such as thrush.
How treatment acts on the mechanism
Metronidazole and clindamycin kill anaerobic bacteria, allowing lactobacilli to recover. Recurrence is common, partly because biofilms persist and lactobacilli may not re-establish. Lactic acid gels help restore acidity. Avoiding douching and perfumed products supports the normal environment.
Research suggests that BV-associated bacteria can be passed between sexual partners, which may explain why BV is linked to new partners and why it often returns after treatment. The biofilm formed by Gardnerella can also shelter bacteria from antibiotics, allowing regrowth once treatment stops. Hormonal changes during the menstrual cycle and pregnancy also influence the vaginal environment.
Types
- Symptomatic BV
- Asymptomatic BV
- Recurrent BV: three or more episodes in a year
Signs and symptoms
- Thin, grey or white vaginal discharge
- Strong fishy smell, especially after sex
- Discharge may increase after a period or sex
- Usually no itching, soreness or redness
- About half of women have no symptoms
Some women notice that the discharge is more watery than usual or that the smell is strongest after sex without a condom. Symptoms can come and go.
How it is diagnosed
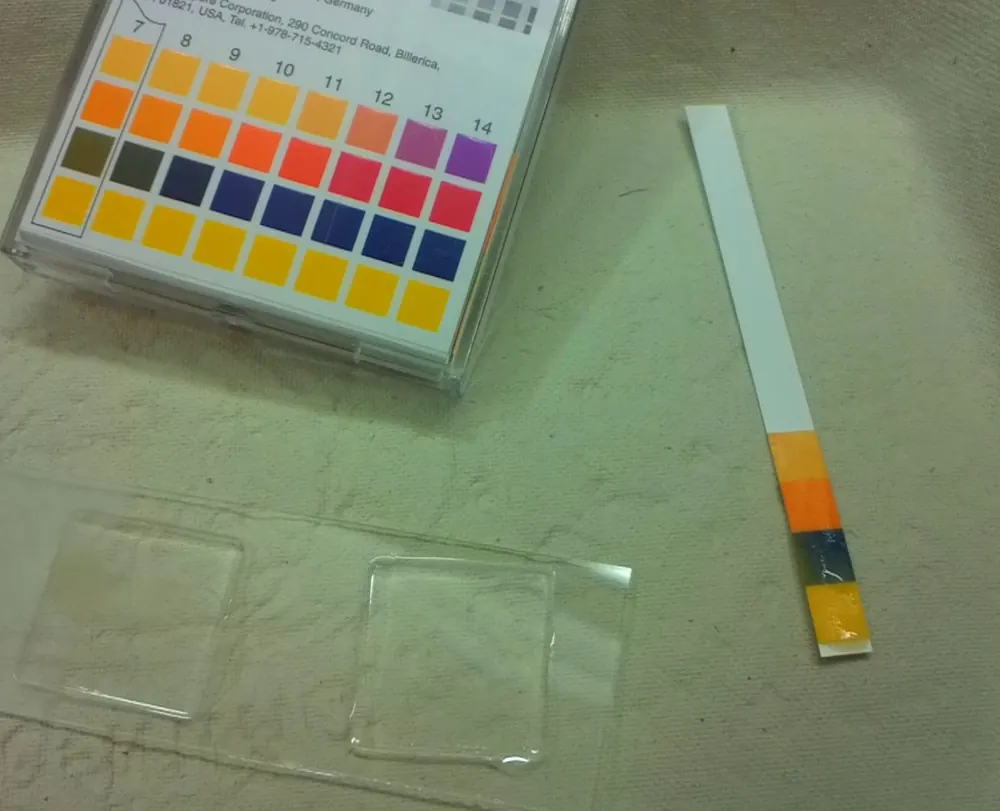
- Clinical assessment using Amsel's criteria: discharge, pH above 4.5, fishy odour when alkali is added (whiff test), clue cells on microscopy
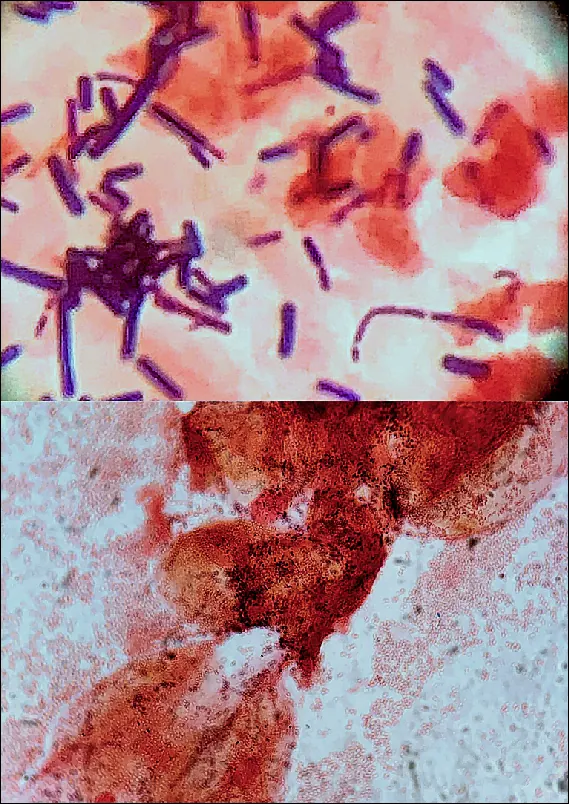
- Gram stain of discharge (Nugent score)
- Vaginal pH test
- Testing for sexually transmitted infections if at risk
Possible complications
- Increased risk of sexually transmitted infections, including HIV
- Pelvic inflammatory disease
- Infection after gynaecological procedures
- In pregnancy: increased risk of preterm birth, late miscarriage and infection of the womb lining after birth
Goals of treatment
Treatment aims to relieve symptoms, restore the normal vaginal environment and reduce recurrence and complications.
Medicines
- Metronidazole tablets or vaginal gel
- Clindamycin cream or tablets
- Tinidazole as an alternative
- Suppressive treatment with vaginal metronidazole gel for recurrent BV
- Lactic acid gel to restore acidity
Alcohol should be avoided during and for 48 hours after taking metronidazole, as it can cause nausea and vomiting. Clindamycin cream can weaken latex condoms.
Other treatments
- Treatment of a female partner if she has symptoms
- Avoiding douching and perfumed products
- Considering a change of contraception if recurrent BV is linked to an IUD
Living with it and prevention
- Avoid douching and vaginal washes
- Wash the vulva with plain water or an unperfumed emollient
- Avoid perfumed bubble baths and soaps
- Use condoms
- Stop smoking
- Change out of damp clothing promptly
Some women find that using condoms consistently and avoiding vaginal products reduces how often BV returns. Probiotics have not been clearly shown to prevent BV.
Monitoring and follow-up
No follow-up is needed if symptoms resolve. Recurrent BV may need suppressive treatment and review.
Outlook
BV usually clears with treatment, but recurrence is common, affecting up to half of women within a year.
Special considerations
- Pregnancy: symptomatic BV should be treated; metronidazole is safe in pregnancy
- Women who have sex with women: BV is common and may be shared between partners
- Before gynaecological procedures: treatment reduces infection risk





